A normal first check cannot rule out problems that develop later, and waiting for symptoms can delay treatment. By following a practical appointment schedule, understanding what each visit and test is for, and recognising when your risk level or symptoms require faster care, you can use ANC more safely and effectively.
Key takeaways
- Book your first ANC visit as soon as pregnancy is confirmed, ideally before 12 weeks.
- Do not stop prescribed medicines without medical advice.
- Keep every scheduled visit so blood pressure, urine, growth, and symptoms are reviewed.
- Seek urgent assessment for severe pain, heavy bleeding, fainting, or reduced fetal movement.
When should ANC begin, and how often should you attend?
Book your first appointment as soon as pregnancy is confirmed, ideally before 12 weeks. This first booking visit establishes gestational age, reviews medical conditions and medicines, identifies concerns such as ectopic pregnancy, and sets the screening plan. Do not stop a prescribed medicine without medical advice.
A practical ANC visit schedule is:
- First trimester: attend the first booking visit, then return around 12 weeks for review and planned screening.
- Second trimester: attend about monthly pregnancy check-ups, usually around 16, 20 and 24 to 26 weeks.
- From 28 to 36 weeks: attend every two weeks, commonly around 28, 30, 32, 34 and 36 weeks.
- From 36 weeks to delivery: attend weekly, with extra visits if symptoms, blood-pressure changes, test results or pregnancy risks require them.
The World Health Organization recommends at least eight ANC contacts, approximately at 12, 20, 26, 30, 34, 36, 38 and 40 weeks. Your clinician may combine or add appointments based on your health, previous pregnancies, twins, high blood pressure, diabetes or fetal-growth concerns.
Regular visits are not only for ultrasound scans: repeated blood-pressure checks, symptom reviews and examination of pregnancy growth create opportunities to find problems before they become urgent.
What happens at a routine ANC appointment?
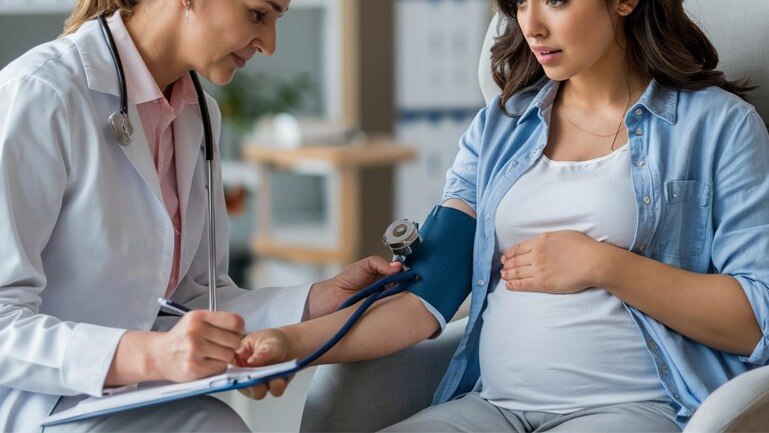
At a routine ANC appointment, a clinician checks your current health, reviews earlier results and assesses whether the pregnancy is progressing as expected. Blood pressure in pregnancy is measured at each visit because pre-eclampsia can begin after 20 weeks without obvious symptoms; a rising reading needs assessment, not just reassurance.
You may be asked about:
- Headache, blurred vision, facial or hand swelling, upper-abdominal pain, bleeding, fluid leakage, contractions and reduced fetal movement.
- Nausea, breathlessness, sleep, mood, anxiety and daily functioning. A positive mental-health screen is not a diagnosis, but it should lead to clinical assessment and safety support.
- Medicines, supplements, smoking, alcohol, nutrition, work and travel. Do not stop a prescribed medicine without discussing the change with the treating clinician.
- Vaccination needs, delivery preferences and plans for postpartum care.
| Check at the visit | What it can reveal |
|---|---|
| Weight review | Unexpected loss, excessive gain or fluid retention that needs context |
| Urine test during pregnancy | Protein, glucose or signs of a urinary infection; testing is not required at every visit |
| Fundal height measurement | Whether uterine growth matches the expected gestational-age pattern; an abnormal trend can prompt an ultrasound |
| Fetal-heart assessment | A present and appropriate fetal heart rate at that appointment |
| Blood tests or scans | Anaemia, blood-group concerns, infection, glucose problems or growth issues when indicated by timing, symptoms or risk |
A urine result or fundal height outside the expected pattern does not diagnose a problem alone; your clinician interprets it alongside symptoms, gestational age and prior measurements.
Which pregnancy tests and ultrasound scans are done, and when?
A first-trimester assessment establishes gestational age, confirms location and viability, and identifies conditions needing early treatment. A normal result does not rule out complications that develop later.
| Examination | What it is intended to detect | Timing and status |
|---|---|---|
| CBC in pregnancy | Anaemia and platelet abnormalities | Early booking; repeat if anaemia, symptoms or risk warrants |
| Blood group and Rh typing | RhD-negative status and antibodies that could affect the fetus or a future pregnancy | Early booking; routine |
| HIV, hepatitis B and syphilis screening in pregnancy | Infections that can pass to the baby and need treatment or prevention | Early booking; repeat testing when risk or local protocol indicates |
| Urine testing | Protein, glucose and urinary infection | At visits when symptoms, blood pressure or risk factors indicate; practice varies |
| Blood-glucose testing | Abnormal glucose regulation | The gestational diabetes test 24 to 28 weeks; earlier and sometimes repeated testing follows previous gestational diabetes or major risk factors |
| Dating or viability ultrasound | Gestational age, heartbeat, location, ectopic pregnancy and molar-pregnancy concerns | Early scan when dates are uncertain, symptoms exist or local care includes it |
| Nuchal-translucency scan | A marker associated with chromosomal conditions, alongside other screening | 11 weeks to 13 weeks 6 days; screening option |
| Anatomy ultrasound | Fetal anatomy, placental location and growth | About 18 to 22 weeks; routine |
| Growth or Doppler ultrasound | Growth, blood flow and placental function | Indication-based, such as fundal-height concerns, hypertension or reduced fetal movement |
Thyroid tests are indication-based, guided by symptoms, history or examination. An ultrasound cannot detect every birth defect or guarantee a healthy baby.
How does regular ANC detect problems before they become emergencies?
A normal result at one visit does not protect you from a condition that develops later. Early detection in antenatal care comes from comparing blood pressure, symptoms, urine, blood tests and fetal measurements over time.
1. Pre-eclampsia monitoring relies on repeated blood-pressure checks and symptom review after 20 weeks. A reading of 140/90 mmHg or higher needs clinical review; 160/110 mmHg or higher is severe. Headache, visual changes, upper-abdominal pain or sudden swelling require urgent assessment, even if your previous readings were normal.
2. A complete blood count can reveal anaemia through a low haemoglobin level, while urine testing and cultures help investigate urinary infection. Screening for HIV, hepatitis B and syphilis identifies infections that need treatment or prevention plans; a positive result requires confirmatory or follow-up testing.
3. Gestational diabetes screening measures glucose, usually at 24–28 weeks. An abnormal screening value does not automatically prove diabetes: the test type, number of abnormal values and laboratory cut-offs determine whether diagnosis is made.
4. Fundal-height measurements that lag behind expected growth can prompt an ultrasound for fetal-growth restriction. Serial ultrasound measurements and Doppler blood-flow studies distinguish a small but healthy fetus from one receiving inadequate placental support.
Screening versus diagnosis in pregnancy matters: screening estimates risk, while diagnosis confirms a condition using defined criteria, repeat testing or specialist assessment. Ask what a result means, whether confirmation is needed, and what action follows.
When does your ANC plan need closer review or urgent assessment?
A history of hypertension, diabetes, kidney disease, thyroid disease, clotting disorders, pre-eclampsia, stillbirth, late miscarriage, preterm birth or repeated caesarean delivery warrants a high-risk pregnancy ANC plan. Twins, triplets, placenta problems, an abnormal scan, or a pregnancy after fertility treatment also require tailored review and specialist coordination.
| Situation | What changes | When to act |
|---|---|---|
| IVF pregnancy monitoring | Confirm fetal number, placental location and growth plan; coordinate obstetric and fertility specialists when needed. | Arrange early review after a positive test. |
| Rh-negative pregnancy | Check blood group and antibody status; discuss anti-D immunoglobulin and extra monitoring after bleeding, injury or procedures. | Confirm the plan at the booking visit. |
| Previous pre-eclampsia or current high blood pressure | Review blood pressure, urine protein, medicines and pre-eclampsia prevention; never start aspirin without clinician advice. | Request an earlier or more frequent schedule. |
| Diabetes, kidney disease or autoimmune illness | Coordinate obstetric care with the relevant physician and adjust medicines safely. | Do not stop prescribed treatment abruptly. |
Seek immediate medical assessment for vaginal bleeding, leaking fluid, severe or persistent abdominal pain, fever, chest pain, difficulty breathing, severe headache, visual disturbance, or sudden swelling of the face or hands. Reduced fetal movement pregnancy warning signs later in pregnancy also require same-day advice; do not wait for the next appointment.
At Thombare Hospital, take your medication list, previous scan reports and treatment history to help the team coordinate care.
Related service
Antenatal (Pregnancy) Check-Up Antenatal (Pregnancy) Check-Up At Thombare Hospital, Dr. Archana Thombare provides comprehensive Antenatal (Pregnancy) Check-Up services to ensure a healthy pregnancy journey. View service → |
Frequently asked questions
When should antenatal care begin?
Book your first ANC appointment as soon as pregnancy is confirmed, ideally before 12 weeks. The visit establishes gestational age, reviews medical conditions and medicines, checks concerns such as ectopic pregnancy, and sets the screening plan.
What happens at a routine ANC appointment?
Your clinician reviews symptoms, medicines, and medical history, then checks measurements such as blood pressure and weight. The appointment also tracks pregnancy progress and identifies changes that need testing or treatment.
Which tests and ultrasound scans are done during pregnancy?
The screening plan depends on gestational age, medical history, symptoms, and earlier results. Your clinician may arrange blood and urine tests, infection screening, blood-group testing, glucose testing, and ultrasound scans at the appropriate pregnancy stages.
How does regular ANC find problems before they become emergencies?
Repeated checks can identify rising blood pressure, abnormal urine findings, anaemia, diabetes, growth concerns, and other changes before symptoms become severe. Early results allow timely treatment, monitoring, referral, or urgent assessment.
When does ANC need closer review or urgent assessment?
Ask for closer review if you have high blood pressure, diabetes, thyroid disease, previous pregnancy complications, multiple pregnancy, or new abnormal test results. Seek urgent assessment for heavy bleeding, severe abdominal pain, fainting, severe headache, vision changes, fluid leakage, fever, or reduced fetal movement.